
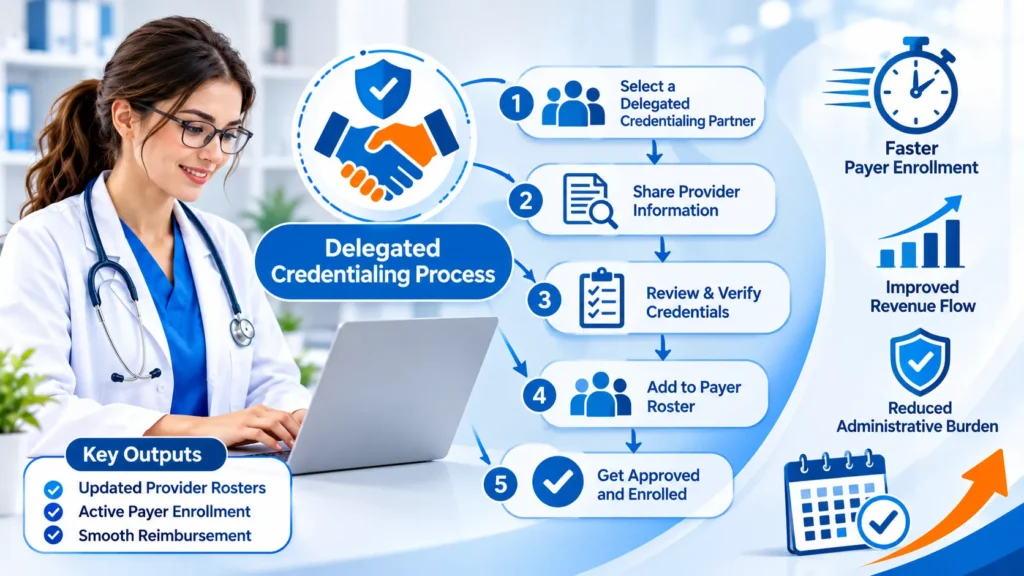
Standard payer credentialing, by contrast, commonly runs 90 to 120 days per payer. That gap is the whole reason groups chase delegation.
This guide walks through how a delegated credentialing program runs from the letter of intent to the annual audit, how roster submission actually works, where the speed comes from, and how delegation plays out for teleradiology groups. You already know the term. Here are the mechanics.
What is the delegated credentialing process?
The delegated credentialing process is the set of steps a health plan and a provider organization follow so the organization can credential practitioners on the plan’s behalf. The plan (the delegating entity) keeps final accountability. Your group (the delegate) runs verification, committee decisions, and ongoing monitoring under a written agreement.
Three pieces hold it together: the delegation agreement, the predelegation evaluation, and ongoing oversight. NCQA’s credentialing standards shape all three. A plan that holds NCQA accreditation has to oversee every delegate, so it writes those NCQA requirements straight into your contract. If your group already uses medical credentialing services for standard enrollment, delegation changes who does the verifying and who makes the call.
Standard payer credentialing vs delegated credentialing
How does a delegated credentialing program run, step by step?
A delegated credentialing program runs in two phases. First you earn delegation: build the program, request it, pass the predelegation audit, and sign the agreement. Then you operate it: credential providers internally, submit rosters, reconcile payer responses, and report to the payer until the next annual audit.
Step 1. Build a program that would pass an audit today
Payers won’t delegate to a group that’s still drafting its policies. Before you call a single plan, you need these pieces running, documented, and dated:
- Written credentialing and recredentialing policies that mirror current NCQA standards
- A credentialing committee that includes participating practitioners for peer review, with minutes that show real discussion of files with adverse findings
- Primary source verification for license, DEA or state CDS registration, board certification, education and training, work history, and malpractice history (including an NPDB query)
- Monthly checks against sanctions and exclusion sources such as the OIG LEIE, SAM, and state Medicaid exclusion lists
- An information integrity policy that controls who can change credentialing data and logs every edit
- Credentialing software that stores verified data once and exports it into each payer’s roster template
- HIPAA compliant storage and transfer for every provider file
Timing rules got tighter, too. Since July 1, 2025, NCQA requires every verification to fall within 120 days of the committee decision for accreditation track organizations, down from 180 days. Certified CVOs now work inside a 90 day window instead of 120.
Step 2. Request delegation from each payer
You negotiate delegation payer by payer. No master agreement covers every plan. Most payers ask for a letter of intent, a predelegation questionnaire, your policies, your committee roster, and recent minutes.
Florida offers a clear example. Sunshine Health, which serves Florida Medicaid and Wellcare members, asks for a letter of intent, its predelegation credentialing questionnaire, a signed delegated credentialing agreement, and a subcontractor addendum, with every signature dated within 30 days of submission.
Step 3. Pass the predelegation audit
The payer audits your policies, committee minutes, and a sample of provider files. Many plans follow the NCQA 8/30 file review method: they pull a random sample of up to 30 files, review the first 8, and expand to the full sample only when they find problems.
Some plans publish a passing score. Canopy Health in California, for one, requires 95 percent or better on both the predelegation audit and the annual oversight audit. If your group or your CVO holds NCQA Credentialing Accreditation or Certification, the payer can give automatic credit on several elements, which shortens this step.
Step 4. Sign the delegation agreement, then wait on the state if Medicaid applies
The agreement spells out exactly what you own. Read it line by line, because auditors will. Expect it to cover:
- Which activities you perform (verification, committee decisions, recredentialing, ongoing monitoring)
- How often you report, at least semiannually under NCQA
- Roster format, cadence, and submission channel
- Remedies for poor performance, up to and including revocation
- Whether you may subdelegate work to a CVO, and with what approval
- How you return or destroy PHI if the agreement ends
Medicaid managed care adds a layer. Sunshine Health sets the delegation effective date at least 90 days after it submits your agreement to Florida’s Agency for Health Care Administration (AHCA), and AHCA’s review can take about that long. Budget a full quarter before your first Florida Medicaid roster goes live.
Step 5. Load the initial full roster
Once the agreement takes effect, the payer asks for a full roster of every practitioner you’ve credentialed. That file becomes the baseline. Reconcile it against the payer’s directory right away, because any mismatch you leave now shows up later as a claim denial.
Step 6. Credential new providers inside your own walls
Here’s where delegation pays. A new hire completes one application, your team verifies everything at the primary source, and your committee decides. The payer doesn’t repeat the work. That provider simply goes on the next roster as an add.
Step 7. Submit rosters on the agreed cadence and reconcile the returns
Most delegated agreements call for a monthly roster, plus ad hoc files for urgent adds and terminations. The next section covers this step in detail, since it’s where most groups lose time.
Step 8. Report, monitor, and face the annual audit
Delegation never runs on autopilot. You send semiannual reports on new providers, terminations, and adverse actions. You run sanctions and exclusion checks every month. You recredential every provider at least every 36 months. And once a year the payer audits you again, usually with another file review.
One recent change helps NCQA accredited and certified delegates. In October 2025, NCQA confirmed that plans receive automatic credit for the semiannual reporting requirement when an NCQA accredited or certified delegate performs the activity.
Keep Your Rosters Clean and Your Providers Loading Faster
Delegation only pays off when the roster side runs clean. A missing taxonomy code or an expired license date can bounce an entire add file and push effective dates back a full cycle. Our provider enrollment team builds payer specific rosters, reconciles every response file, and tracks effective dates by payer. Talk with us about getting your new providers loaded faster.
How do you submit delegated credentialing rosters to payers?
You submit delegated credentialing rosters as a payer formatted file, usually an Excel or CSV template, through the payer’s portal, secure email, or SFTP on a set cadence, most often monthly. Each row carries one action (add, change, or term), an effective date, and the provider’s identifiers, licenses, locations, and credentialing dates.
No national roster standard exists. Every payer publishes its own template, column order, and date format, so a group delegated with eight plans maintains eight versions of the same provider data.
What goes on a delegated credentialing roster?
How does the monthly roster cycle work?
- Set a cutoff, such as every committee approval through the 25th of the month.
- Export provider data from your credentialing system into each payer’s current template.
- Validate every row: NPI against NPPES, license and DEA status, exclusion checks, and address consistency with CAQH.
- Submit through the payer’s required channel and log the timestamp plus any ticket or case number.
- Wait out the processing window, which payers commonly quote at 15 to 30 days.
- Reconcile the payer’s response or error file and resubmit any rejected rows in the next cycle.
- Confirm the provider shows as participating in the payer’s claims system and directory before you schedule patients.
Why do payers reject roster rows?
- Data on the roster doesn’t match CAQH or NPPES (a suite number, a middle initial, a retired location)
- A license or DEA registration expires before the payer finishes processing
- The group used an outdated template. Payers change formats without much notice: Aetna Better Health of Oklahoma, for example, moved all roster updates to its Contact Us form in 2026 and stopped accepting them by email
- Taxonomy codes or service locations sit blank
- The row requests a retroactive effective date the agreement doesn’t allow
If you see the same rejection two months running, fix the source data in your credentialing system, not the spreadsheet. Spreadsheet patches come back every cycle.
How do delegated credentialing rosters speed up payer enrollment?
Delegated credentialing rosters speed up payer enrollment by removing the payer’s own credentialing review. The payer accepts your committee’s decision, so the roster only has to clear data loading. That turns a 90 to 120 day credentialing wait into a processing window that payers often quote at 15 to 30 days.
Think about where the standard timeline goes. A payer receives your application, pulls CAQH, runs its own primary source verification, waits for its committee (often a monthly meeting), and then loads the contract. Delegation deletes the middle three steps.
It also collapses the volume. Without delegation, one new physician joining a group with 10 payer contracts means 10 separate credentialing reviews. With delegation across all 10, it means one internal file and 10 roster rows.
A worked example
Picture a 14 provider orthopedic group in Tampa hiring a spine surgeon who starts August 1. The group holds delegation with four of its six commercial payers. Its committee approves the surgeon on July 10, the July roster closes on the 25th, and those four payers have 15 to 30 days to process. The surgeon could plausibly reach in network status with all four by late August.
The two nondelegated payers still run their full reviews, which can stretch past the 90 day mark. That’s normal. Delegation rarely covers every payer, and you should plan staffing around both tracks. Our breakdown of what a credentialing delay costs per provider shows why those remaining weeks matter.
What delegation does not speed up
- Traditional Medicare enrollment. CMS doesn’t delegate it, so you still file through PECOS on its own timeline. Our guide to Medicare enrollment through PECOS covers that track.
- State Medicaid fee for service enrollment, which runs through each state’s own provider portal
- Contract negotiation and fee schedule review
- Hospital privileges, which follow medical staff bylaws instead of payer agreements
Medicare Advantage plans can delegate credentialing to your group. Traditional Medicare can’t.
What is accelerated delegated credentialing?
Accelerated delegated credentialing is an industry phrase, not an NCQA category. It describes a delegated program tuned to move providers from signed offer to roster in the shortest compliant window. The work starts earlier, the committee meets more often, and rosters leave on a fixed cutoff instead of whenever someone finds time.
What does that look like in practice?
- Start primary source verification the day the offer letter comes back signed, not on the start date
- Let your medical director approve clean files between committee meetings, if your policy allows it
- Align the roster cutoff with the committee calendar so approvals never wait an extra month
- Keep every profile reattested on the 120 day cycle by keeping CAQH profiles current, because roster data that conflicts with CAQH triggers rejects
One trap: start too early and the verifications expire. Under NCQA’s 120 day limit, your team has to reverify anything older than 120 days at the committee decision. Early is good. Six months early isn’t.
How does delegated credentialing work in teleradiology?
Delegated credentialing in teleradiology usually means two separate arrangements. Hospitals use credentialing by proxy to rely on the teleradiology group’s credentialing for medical staff privileges. Payers use delegated credentialing to accept the group’s roster for network participation. Most teleradiology groups need both.
The hospital side: credentialing by proxy
CMS Conditions of Participation at 42 CFR 482.12(a)(8) and (a)(9) let a hospital’s governing body grant privileges based on the credentialing decisions of a distant site hospital or telemedicine entity, such as a teleradiology group. A written agreement has to back the arrangement, and the originating hospital still shares performance and adverse event information with the distant site.
The Joint Commission runs its own proxy standard and expects both organizations to hold Joint Commission accreditation for it to apply. A few states restrict proxy arrangements, so check state hospital licensure rules before you sign. If your readers need medical staff privileges at each reading hospital, proxy agreements cut that paperwork sharply, though they don’t erase it.
The payer side: rosters across many states
A teleradiologist reads studies for patients in many states and needs a license in each patient’s state. The Interstate Medical Licensure Compact speeds that up for physicians, but every license still lands on the roster with its own number and expiration date.
Volume is the real argument here. A teleradiology group adding three readers a month across 20 payer contracts faces 60 separate applications under standard credentialing. Under delegation, it faces three committee files and a set of roster rows.
Watch for these teleradiology specific roster problems:
- One of a reader’s many state licenses expires and blocks the whole row
- Some state Medicaid plans require in state enrollment details the roster template doesn’t capture
- Non patient facing radiologists show up in member directories as bookable unless you ask each payer how to flag them
- Hospital privileges lapse at an originating site while payer participation stays active
Clean credentialing also protects downstream claims, which matters when you outsource billing for your radiology reads and want every read paid at in network rates.
Is a delegated credentialing program worth it for your group?
A delegated credentialing program is worth it when your hiring volume and payer concentration justify the audit workload. It works best for groups that add providers every month, hold contracts with a few payers that carry most of their revenue, and already run a credentialing committee.
Here’s our honest take. Most groups chase delegation before their committee minutes could survive an audit. If your practice adds only a handful of providers a year, a tight standard credentialing process with clean CAQH profiles and weekly payer follow up will beat a delegation agreement you can barely maintain.
Smaller practices have another route, too. Many independent physicians reach delegated status by joining an IPA or health system that already holds delegation with the major plans.
Mistakes that cost groups their delegation
- Committee minutes that list approvals but never show discussion of files with adverse findings
- Verifications that age past 120 days before the committee decides
- Skipped monthly sanctions and exclusion checks, even for one month
- Handing work to a CVO without the payer’s written approval to subdelegate
- Late or incomplete semiannual reports
Fail an annual audit and the payer issues a corrective action plan. Fail the follow up review and it can revoke delegation, which sends every new provider back to a full individual application.
Where should your group start?
Start with an honest file review. Pull ten recent provider files, check every verification date against the 120 day window, and read your last three committee minutes the way an auditor would. Whatever breaks there will break in the predelegation audit.
Make Your Program Audit Ready Before the Payer Arrives
Delegation stalls when a program isn’t audit ready the day the payer arrives. Our medical credentialing team reviews your policies, committee minutes, and provider files against current NCQA standards, then manages roster builds and payer follow up for delegated and nondelegated plans alike. Let’s map the fastest path to accelerated payer enrollment for your providers.
Frequently asked questions about the delegated credentialing process
How long does it take to set up a delegated credentialing program?
Expect several months per payer. Policy work, the predelegation audit, and contract signatures each take time, and Medicaid managed care plans may need state approval on top. In Florida, Sunshine Health sets the delegation effective date at least 90 days after it submits the agreement to AHCA, and AHCA’s review can take about that long.
Does delegated credentialing replace payer enrollment?
No. Delegation replaces the payer’s credentialing review, not the rest of enrollment. You still need a signed contract, a correct load in the payer’s claims system, and an accurate directory listing. Traditional Medicare enrollment through PECOS and state Medicaid fee for service enrollment stay outside delegation entirely.
Is a CVO the same as delegated credentialing?
No. A credentials verification organization (CVO) verifies credentials at the primary source, but it doesn’t make the credentialing decision. Under delegation, your committee decides. Your group can still use a CVO for verification work, as long as the payer approves that subdelegation in writing.
How often do you submit a delegated credentialing roster?
Most payers want a roster every month, plus additional files as needed for urgent adds, changes, and terminations. Sunshine Health, for example, asks delegated groups for monthly rosters and allows up to 30 days to process each submission. Your delegation agreement sets the exact cadence and channel.
Can a small practice get delegated credentialing?
Rarely on its own. Payers expect enough provider volume to justify the oversight, plus a functioning credentialing committee. Small practices usually get similar speed by joining an IPA or health system that already holds delegation, or by tightening standard credentialing with clean CAQH profiles and weekly payer follow up.
What happens if you fail a delegation audit?
The payer typically issues a corrective action plan with deadlines. If the follow up review still finds gaps, the payer can revoke delegation under the remedies section of your agreement. After revocation, every new provider goes back to a full individual credentialing application with that payer.
What changed in delegated credentialing for 2025 and 2026?
NCQA standards that took effect July 1, 2025 cut the verification window to 120 days for accreditation track organizations and 90 days for certified CVOs, and added monthly monitoring and information integrity expectations. In October 2025, NCQA also gave plans automatic credit for semiannual reporting from NCQA accredited or certified delegates.
Do teleradiologists need privileges at every hospital they read for?
Yes, each originating hospital grants privileges, but credentialing by proxy lets that hospital rely on the teleradiology group’s credentialing decisions under 42 CFR 482.12(a)(8) and (a)(9). A written agreement must support the arrangement, and the hospital still shares performance and adverse event information with the group.
Sources: NCQA practical guidance on delegation for health plans; 42 CFR 482.12 governing body requirements, including telemedicine credentialing; National Practitioner Data Bank; Sunshine Health delegated credentialing process.
