Key takeaways
- A health plan (the delegator) hands credentialing work to a provider organization (the delegate) through a written delegation agreement.
- Delegates follow NCQA standards. Since July 1, 2025, that means primary source verification within 120 days under Credentialing Accreditation and 90 days under Credentialing Certification.
- Delegation doesn’t replace Original Medicare PECOS enrollment, state Medicaid screening, hospital privileges, or your payer contract.
- Most independent practices won’t qualify. Plans often set roster minimums in the hundreds of providers.
What is delegated credentialing?
Delegated credentialing means one organization does the credentialing work another organization would normally do itself. In healthcare, the health plan almost always hands the work off, and a large provider organization picks it up.
Delegated credentialing meaning in plain English
Run the math without delegation. A 300 provider multispecialty group contracts with 9 commercial and Medicare Advantage plans. Each plan credentials every provider separately, so the group’s staff builds, tracks, and chases 2,700 individual credentialing files. Every one of those plans checks the same medical license with the same state board.
Delegation collapses that work. The group credentials each provider once through its own NCQA aligned program, then sends each delegating plan a roster. Same verification. One file per provider instead of nine.
Delegation is one model inside the larger world of medical credentialing services, and most practices only ever deal with the standard, payer by payer model.
What do people mean by “delegated credentials”?
You’ll hear providers say they hold “delegated credentials.” That’s shorthand. It means a delegate organization credentialed them on a plan’s behalf, so their in network status with that plan runs through the delegate’s agreement instead of a direct application. That detail matters a lot if the provider ever changes jobs, and we cover it below.
Who are the parties in a delegated credentialing arrangement?
Every arrangement has a delegator and a delegate. Many add a third party, a subdelegate, that handles verification tasks without making decisions.
How does delegated credentialing work?
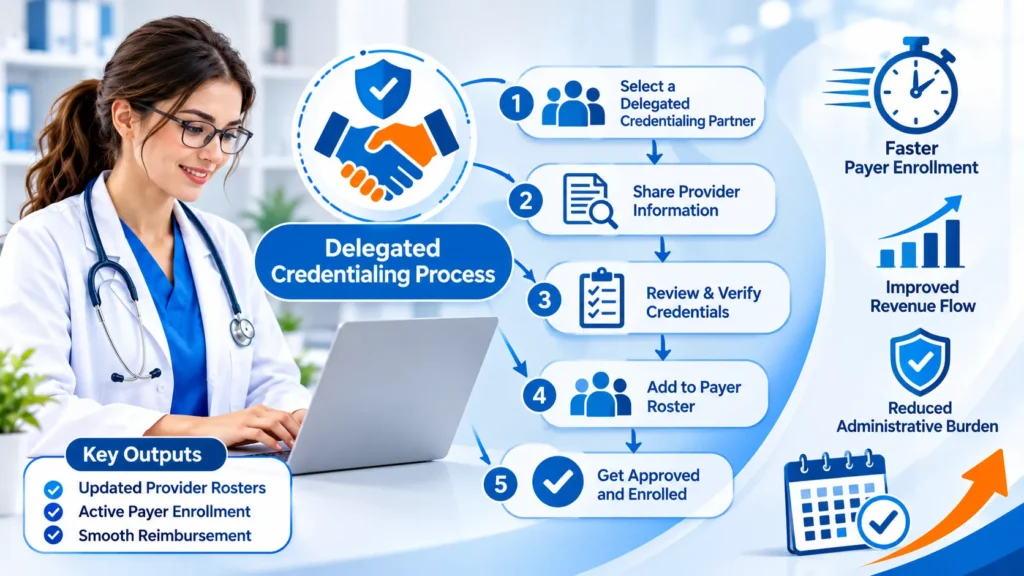
Delegated credentialing works in six stages. The provider organization builds an NCQA aligned program, the health plan audits it, both sides sign a delegation agreement, the delegate credentials providers and submits rosters, the plan audits the delegate every year, and either side fixes gaps through corrective action.
- Build the program. Written credentialing policies, a credentialing committee that includes participating practitioners, verification procedures, secure file storage, and ongoing monitoring. Most plans want to see real, completed files, not just a policy binder.
- Pass the pre delegation audit. The plan reviews your policies, committee minutes, and a sample of credentialing and recredentialing files against NCQA file review elements. Gaps here stall everything that follows.
- Sign the delegation agreement. The agreement spells out which functions transfer, how often you report, the plan’s audit rights, subdelegation rules, and what happens if performance slips. Some plans attach it to the participation contract. Others use a standalone document.
- Credential providers and submit rosters. Your committee approves providers, then you send each plan a roster (often monthly) listing additions, terminations, and demographic changes. The plan loads those providers into its claims and directory systems.
- Pass the annual oversight audit. The plan rechecks your files every year. Blue Cross and Blue Shield of Kansas, for example, audits delegates within 60 days of signing and then every year, with a 90 percent file score expectation.
- Fix findings or lose delegation. Audit findings trigger a corrective action plan. Repeated failures can end the arrangement, and the plan takes credentialing back in house.
Stage 4 is where billing teams feel the pain. A plan’s credentialing approval and the date its claims system recognizes the provider are two different dates. Say your roster goes out on the 5th and the plan loads it on the 28th. Claims for visits in between can come back on the ERA with CARC B7 (provider not certified or eligible for this service on this date of service). Track the load date, not the committee date.
Delegated vs non delegated credentialing: what is the difference?
The difference comes down to who verifies and who decides. In standard (non delegated) credentialing, the health plan does both. In delegated credentialing, the provider organization does both, and the plan supervises.
Here’s our take. Software vendors pitch delegation as the fast lane, and for big organizations it often is. It doesn’t make credentialing lighter, though. It moves the whole workload, plus the audit exposure, onto your payroll.
If your practice runs the standard model, the biggest speed lever sits on your side of the table: keeping a current CAQH profile so every payer pulls clean data the first time.
Get New Providers Credentialed Without the Wait
A new physician who sits idle while payers work through applications one at a time costs your practice real revenue. Our physician credentialing services handle CAQH setup, primary source verification, and parallel applications to every payer you need, with weekly status updates on each one. Talk with our team about your next provider start date.
What are the NCQA requirements for delegated credentialing in 2026?
NCQA expects a delegate to run the same credentialing program a health plan would run: written policies, a peer committee, primary source verification inside a fixed window, recredentialing at least every 36 months, and monitoring between cycles. The delegating plan must audit all of it.
- Verification windows. Since July 1, 2025, organizations under NCQA Credentialing Accreditation get 120 days (down from 180) between verification and the credentialing decision. Credentialing Certification organizations, typically CVOs, get 90 days.
- Recredentialing at least every 36 months. The delegate owns the cycle, and some plans write shorter intervals into the agreement.
- Ongoing monitoring. Delegates check Medicare and Medicaid sanctions, OIG exclusions, SAM.gov, license actions, and member complaints between cycles instead of waiting for recredentialing.
- Committee review and documentation. A credentialing committee with participating practitioners reviews any file that doesn’t meet clean criteria, and every file shows dates, sources, and who verified each element.
- Primary sources. Delegates verify directly with state licensing boards, the National Practitioner Data Bank, board certification sources such as ABMS, and DEA records.
- Data integrity controls. NCQA now expects written controls that protect credentialing data from inappropriate changes, plus monitoring and reporting on any changes that do happen.
Federal rules that sit on top of NCQA
NCQA isn’t the only rulebook. Medicare Advantage plans follow 42 CFR 422.504(i), which lets an MA organization delegate functions to first tier and downstream entities while keeping the MA organization accountable to CMS for everything those entities do. Medicaid managed care plans follow 42 CFR 438.214 for credentialing and 438.230 for subcontracting and delegation. State insurance departments and Medicaid agencies add their own requirements on top.
What doesn’t delegated credentialing cover?
Delegation covers a plan’s credentialing decision. It doesn’t replace government enrollment, hospital privileges, or your contract with the plan.
- Original Medicare enrollment. Traditional Medicare doesn’t delegate credentialing. Every provider still enrolls with the Medicare Administrative Contractor through PECOS or the CMS-855 forms. If you’re new to that process, here’s how to enroll in PECOS step by step.
- State Medicaid screening. Under 42 CFR 438.602(b), each state must screen and enroll every network provider of its Medicaid managed care plans, even when the MCO delegates its own credentialing.
- Hospital privileges. A hospital’s medical staff office grants clinical privileges through a separate process with its own bylaws and committees. Delegated payer credentialing never stands in for privileges at the hospital.
- Payer contracts and fee schedules. The group still negotiates its participation agreement. Delegation changes who credentials, not what the plan pays.
One more trap. Delegated providers usually still need a CAQH profile, because their other payers (the ones without a delegation agreement) pull from it. It’s common for a practice to let a profile lapse because “the system handles credentialing,” then lose months with a non delegated plan.
Who qualifies for delegated credentialing?
Health plans usually offer delegation only to organizations big enough and mature enough to run an NCQA level program. Each plan sets its own bar.
Size thresholds vary. Blue Cross and Blue Shield of Kansas requires delegates to keep at least 250 providers on the roster under its 2026 delegation policy. Other plans look for NCQA Credentialing Accreditation, a history of clean audit scores, and dedicated credentialing staff, often with CPCS or CPMSM certification from NAMSS. Organizations that tend to qualify include:
- Health systems and hospital owned physician groups
- IPAs and ACOs contracting on behalf of hundreds of providers
- Large single specialty or multispecialty groups
- MSOs that run credentialing for affiliated practices
- Telehealth companies credentialing providers across many states
If you manage a 6 provider family medicine practice in Tampa, delegation almost certainly isn’t on the table. That’s fine. Your fastest path is a complete standard application to every payer at once, a CAQH profile that never goes stale, and someone who follows up every week.
What happens when a delegated provider leaves the organization?
Their credentialing usually stays behind. Network status under delegation belongs to the delegate’s agreement, so when employment ends, the delegate terms the provider from its rosters and each plan drops them.
Picture a common scenario. A nurse practitioner leaves a hospital owned primary care group and joins an independent dermatology practice. She tells the office manager she’s “already credentialed” with two of her biggest commercial plans. She was, under the health system’s delegation. Two weeks into the new job, her claims start bouncing, because neither plan ever credentialed her directly.
You can head this off with three habits:
- Ask every new hire whether any current payer participation runs through a delegated group.
- Start standard credentialing 90 to 120 days before the start date for every payer in that situation.
- Confirm the termination date the old group sends on its roster, so you can plan around any coverage gap.
Some providers keep both arrangements at once: delegated status through a health system and direct credentialing for a private practice. Plans allow it, but each relationship needs its own file and its own effective date. Every week of overlap you miss shows up as lost visits, and we broke down what a stalled application really costs a practice in a separate guide.
What are the pros and cons of delegated credentialing?
Delegation trades payer dependency for internal workload. It speeds onboarding and hands the organization control, but it adds audit exposure and permanent staffing costs.
Benefits
- Faster network participation. Providers join plan rosters on the delegate’s schedule instead of waiting in each payer’s queue.
- One verification per provider. The organization verifies once and reuses the file across every delegating plan.
- Control over priorities. The group decides which providers move first, such as a surgeon with a full OR block next month.
- A better provider experience. New hires fill out one internal application instead of a stack of payer forms.
Drawbacks
- Fixed overhead. Committee time, credentialing software, trained staff, and CVO fees cost money whether you’re hiring or not.
- Audit fatigue. Every delegating plan brings its own audit tool, reporting template, and calendar.
- Portability problems. Providers lose delegated status when they leave, as covered above.
Close the Enrollment Gaps That Hold Up Your Claims
Delegation doesn’t cover Medicare PECOS, state Medicaid enrollment, or plans that credential directly, and those gaps hold up claims. Our provider enrollment services handle CMS-855 filings, Medicaid enrollment, NPI setup, and commercial payer applications so your new providers start billing sooner. Reach out to plan your next enrollment.
So, is delegated credentialing right for your practice?
For a health system or a 300 provider IPA, delegation usually pays for itself through faster onboarding and less payer back and forth. For most independent practices, the smarter play is fast, complete standard credentialing with tight tracking. Either way, expect your providers to touch both models over their careers, and plan your onboarding around that.
Frequently asked questions about delegated credentialing
Does delegated credentialing replace payer enrollment?
No. Delegation covers verification and the credentialing decision. Your group still needs a participation agreement with the plan, the plan still loads each provider from your roster before claims pay, and Original Medicare and state Medicaid enrollment stay completely separate.
Is delegated credentialing the same as using a CVO?
No. A CVO verifies credentials and hands back a file, but it doesn’t decide who joins the network. A delegate makes that decision through its own committee. Many delegates hire an NCQA certified CVO as a subdelegate for verification work and keep decision authority in house.
How long does it take to become a delegated entity?
Plan on several months at minimum. You need working policies, an active committee, and real completed files before a plan schedules a pre delegation audit, and each plan negotiates its own agreement. Timelines vary by payer and by how audit ready your files are.
Can small practices get delegated credentialing?
Rarely. Plans set minimum roster sizes (Blue Cross and Blue Shield of Kansas requires 250 providers) and expect an NCQA level program. Small practices usually move faster by sending complete standard applications to every payer in parallel and keeping CAQH current.
Who is responsible if a delegate credentials a provider incorrectly?
Both parties carry exposure. The delegate faces corrective action or loss of delegation, and the health plan stays accountable to NCQA, CMS, and state regulators for its network. That shared accountability explains why plans audit delegates every year and why most agreements spell out remediation steps in detail.
Does the health plan give up control under delegation?
No. The plan keeps final authority over its network. It can reject or remove a provider the delegate approved, require a corrective action plan, and revoke the delegation agreement entirely. In practice, plans rarely overrule clean files, but the authority never transfers.
Can a provider have both delegated and traditional credentialing?
Yes. A provider can hold network status through a health system’s delegation and, separately, through direct credentialing for a private practice. Each arrangement needs its own application, file, and effective date with the plan, so track both and never assume one covers the other.
What is subdelegation in credentialing?
Subdelegation happens when a delegate hands part of its delegated work, usually primary source verification, to another organization. Most delegation agreements require the plan’s written approval first and require the delegate to audit its subdelegate, usually every year, using the same file review standards the plan applies.
How often does recredentialing happen under delegation?
NCQA requires recredentialing at least every 36 months. The delegate runs that cycle plus the ongoing monitoring between cycles, and some plans set shorter intervals in the delegation agreement. A missed recredentialing date can drop a provider from the roster, so delegates track every due date centrally.
What is a delegated roster?
A delegated roster is the provider list a delegate sends each health plan, usually monthly, showing new providers, terminations, and demographic changes. The plan loads providers into its claims and directory systems from that roster, so roster errors turn into claim denials fast.
Does Medicare use delegated credentialing?
Medicare Advantage plans can delegate credentialing under 42 CFR 422.504(i), and the MA organization stays accountable to CMS. Original Medicare doesn’t delegate. Every provider still enrolls through PECOS or the CMS-855 forms with their Medicare Administrative Contractor, regardless of any delegation agreement.